

A complete therapy intake form captures five things: identifying and emergency contact data, the presenting problem and clinical history, a safety screen for suicidality and harm risk, informed consent (including telehealth consent), and billing or insurance details. This article gives you copy-ready fields, conditional-logic suggestions, and practical HIPAA guidance for sending these forms digitally before session one.
TL;DR:
- Digital intake forms reduce administrative friction by routing clients with safety concerns directly to clinicians, improving pre-session safety review.
- HIPAA-compliant texting platforms are essential for sending appointment reminders and intake communications containing PHI, with encryption and client consent.
- Intake forms should be customized for client type, including minors, couples, family therapy, and telehealth, with specific fields like guardian consent and session location.
- Forms should be sent automatically 24 to 72 hours before sessions, with conditional logic guiding routing based on responses to streamline the process.
- Regularly updating intake forms annually or after policy changes ensures compliance with evolving state laws, safety procedures, and practice needs.
Table of Contents
- What Is a Therapy Intake Form, and Why Does It Matter?
- What Fields Belong on a Therapy Intake Form?
- Are Appointment Reminders and Intake Texts HIPAA Compliant?
- Which Intake Fields Change by Client Type?
- When Should You Send an Intake Form, and How?
- How Do You Build a Copy-Ready Intake Form Template?
- What Do Clinicians Notice After Switching to Digital Intake?
- What Legal Rules Apply Beyond HIPAA?
- How Should You Store and Secure Intake Data?
- Should Intake Forms Differ by Therapeutic Modality?
- How Often Should You Update Your Intake Form?
- The Template Trap Most Practices Fall Into
- Automate Intake Delivery Without Losing the Clinical Detail
- Sources
What Is a Therapy Intake Form, and Why Does It Matter?
A therapy intake form is the document that does three jobs at once: clinical intake, safety triage, and informed consent. It gathers the history a clinician needs to plan treatment, screens for immediate risk before the client walks into (or logs onto) the first session, and secures the signatures required to treat legally and ethically.
Paper forms handed over a clipboard still do this job, technically. But they force clients to disclose sensitive details in a waiting room, they cannot branch based on an answer, and they sit in a filing cabinet instead of a chart. Digital forms fix all three problems. A client answering “yes” to a self-harm question on a phone screen can be routed straight to a flagged clinician dashboard rather than waiting for someone to read a paper stack. That single design choice is why digital intake workflows improve pre-session safety review compared with static paper.
Digital intake templates typically live in one of two places:
- Inside an EHR, where responses auto-populate chart fields and reduce duplicate data entry.
- Inside a standalone secure form builder, which offers more design flexibility but requires manual or API syncing into the record.
Where you host the form changes how much administrative friction your practice carries for the life of every client file.
What Fields Belong on a Therapy Intake Form?
Building an intake form from scratch is easier with a field-by-field checklist in front of you. Use this as your master list, then trim or expand based on your setting.
- Contact and demographics. Full legal name, date of birth, address, phone, preferred pronouns, and a dedicated emergency contact with relationship and phone number. Ask explicitly whether the emergency contact can be told the client is in therapy. That single line prevents an awkward call later.
- Presenting concern and history. A short open-text field (“What brings you to therapy right now?”) paired with checkboxes for prior therapy, current medications, relevant medical conditions, and family mental health history. Keep the open-text box first. Clients write more honestly before they see a wall of checkboxes.
- Symptom screening. Include a brief validated screener where clinically appropriate. Full instruments like the PHQ 9 or GAD 7 belong on their own page or can wait for session two if the presenting concern doesn’t warrant them at intake.
- Safety screening. Ask directly about current suicidal ideation, self-harm, and thoughts of harming others. Build branching logic so a positive response triggers an immediate task for the clinician, not a routine chart note. Document a next-step checklist: call the client, review a safety plan, or route to a crisis referral before the scheduled appointment.
- Consent. Informed consent for treatment, a specific telehealth consent block if sessions happen remotely, a cancellation and no-show policy, a HIPAA privacy notice acknowledgment, and an e-signature field.
- Insurance and billing. Insurance carrier, member ID, group number, and a credit card authorization if you collect payment on file.
- Communication preferences. A documented opt-in for text or email contact, separate from the consent-to-treat signature.
Pro Tip: Put the safety screening questions on their own page instead of burying them mid-form. Clients answer more honestly when a question doesn’t feel attached to twenty others, and your conditional logic is easier to build when the safety block is isolated.
Are Appointment Reminders and Intake Texts HIPAA Compliant?
Standard SMS is not built for protected health information. Consumer texting apps route messages through carrier servers without encryption, and texting PHI is compliant only through a vendor that has signed a Business Associate Agreement providing the required administrative and technical safeguards. That is the line every practice needs to know before automating anything.
Appointment reminders themselves are usually fine. A text containing only the date, time, and location does not violate HIPAA. What crosses the line is including a diagnosis, a treatment detail, or a balance owed. When a patient asks for an alternative communication method, that request should be documented under 45 CFR 164.522(b), and honored going forward.
The American Psychiatric Association’s own guidance backs this up: email and text are usable tools, provided you apply reasonable safeguards and use a HIPAA-compliant vendor with a BAA for anything beyond minimal scheduling content.
Practical steps that hold up under audit:
- Route intake forms and clinical messages through a HIPAA-compliant speech to text platform, never a personal cell phone.
- Limit unencrypted SMS strictly to time and location reminders.
- Document each client’s communication preferences at intake, including consent for any non-encrypted channel.
- Train front-desk staff on what content is never allowed in a text, regardless of the vendor.
The 45 CFR 164.522(b) provision on documenting alternative communication requests is a small line in a large regulation, but it is the one most practices forget until a client complains. Consult a compliance attorney or HIPAA specialist for anything outside these baseline rules, especially multi-state or group practices.
Which Intake Fields Change by Client Type?
A base template does not fit every client. Couples, families, minors, and telehealth clients each need specific additions rather than a bigger generic form.
- Couples and family therapy: clarify who completes the form (each partner separately, or one shared submission), add a relationship history section, and state confidentiality limits between partners in writing before the first session.
- Minors: add guardian consent language, custody or legal-guardianship details, a parent or guardian contact field, and age-appropriate assent language for the minor themselves.
- Telehealth: capture the client’s physical location at the time of each session (this determines licensure jurisdiction), an emergency contact who is local to that same location, and a specific telehealth informed consent block covering technology limits and emergency protocols.
For substance use or trauma-focused practices, add a dedicated specialty form rather than cramming five extra questions into the base intake. A short screening item (“Has substance use been a concern in the past year?”) is enough at first contact; the deeper assessment belongs in its own document.
When Should You Send an Intake Form, and How?
Timing determines whether your form gets completed or ignored. Send it at the moment of booking, not the day before.
- Trigger the intake form automatically when the appointment is booked, with a clear deadline: 24 to 72 hours before the session.
- Use conditional logic so low-risk answers skip irrelevant follow-up questions, shortening completion time and keeping high-risk answers routed straight to a clinician task list.
- Sync completed fields directly into chart notes and billing records. Automated distribution and pre-filling is what separates a modern intake workflow from one that just moved paper onto a screen.
- Build a follow-up step for incomplete or flagged forms: an automated reminder for the former, a same-day clinician call for the latter, before the client ever sits down.
How Do You Build a Copy-Ready Intake Form Template?
Group your fields into five sections when you build this out in a Google Form, PDF, or EHR builder: identifying information, clinical history, safety screening, consent, and billing. That order matters because it moves from low-stakes to high-stakes questions, which keeps clients engaged instead of shutting down on page one.
Add conditional logic at two points specifically: right after the safety screening questions (route positive responses to a clinician alert) and right after the telehealth location question (route out-of-jurisdiction answers to a scheduling hold). Widely used templates combine these elements into one flow, but always adapt the language to your state’s licensure requirements rather than copying verbatim.
For distribution, a PDF with e-signature works for smaller practices; a secure form with webhook integration into your EHR scales better once you’re onboarding several clients a week.
What Do Clinicians Notice After Switching to Digital Intake?
Practices that move from paper to automated, pre-filled intake typically report fewer duplicate entries and faster chart prep before session one. Mobile-friendly forms and voice-agent support also open intake to clients who can’t easily fill out a paper packet, including visually impaired clients.
Author credentials, case studies, and practice testimonials to be added.
What Legal Rules Apply Beyond HIPAA?
HIPAA sets the federal floor, but it is not the ceiling. State licensure boards often impose their own record-keeping and consent requirements that are stricter than federal law, and these vary enough that a form built for a California practice may be missing required language for a Texas one.
Minor consent law is the clearest example. Some states allow adolescents above a certain age to consent to their own mental health treatment without parental sign-off for a limited number of sessions; others require guardian consent regardless of age except in narrow circumstances like reporting abuse. Your intake form’s guardian consent block needs to reflect your specific state’s rule, not a generic assumption.
Mandatory reporting language deserves its own line item too. Most states require clinicians to disclose, at intake, the limits of confidentiality around suspected child abuse, elder abuse, and imminent danger to self or others. Burying this in a dense privacy notice is technically compliant in many states but ethically thin. Put it in plain language, in its own short paragraph, and have the client initial it separately from the general consent signature.
Telehealth adds a second layer: many states require the clinician to be licensed in the state where the client is physically located during the session, not just where the practice is based. If you see telehealth clients across state lines, your intake form needs a location-verification field for every single session, not just the first one.
None of this replaces legal counsel. A practice attorney or your state licensing board’s own published guidance should be the final word on anything your intake form states about consent, mandatory reporting, or minor treatment rights.

How Should You Store and Secure Intake Data?
Once a client submits an intake form, where that data lands matters as much as what’s on the form. Loose PDFs sitting in a shared inbox are a liability regardless of how carefully the questions were written.
Store completed forms inside a system with encryption at rest and in transit, role-based access controls, and an audit trail showing who viewed or edited a record and when. If your form builder or EHR doesn’t offer all three, treat that as a signal to switch platforms rather than as an acceptable gap.
Access should be limited to staff who need it for treatment, payment, or operations, and nothing broader. A receptionist scheduling appointments doesn’t need to see the safety screening answers; a billing contractor doesn’t need to see the clinical history. Segmenting access by role reduces exposure if any single account is compromised.
Back up intake records on a schedule and test that the backup actually restores, not just that it runs. And set a retention and deletion policy that matches your state’s record-retention requirements, since keeping data indefinitely “just in case” is its own compliance risk once a client formally requests deletion or transfer of records.
Should Intake Forms Differ by Therapeutic Modality?
A cognitive behavioral practice and a psychodynamic one don’t need identical intake forms, even though both need the same core safety and consent fields. The additions should reflect what each modality actually treats first.
CBT and solution-focused practices benefit from adding a brief goals section: what specific behavior or symptom the client wants different in the next three months. That single field gives the clinician a baseline to measure progress against from session one.
Psychodynamic and relational practices often add a fuller developmental and family-of-origin history section, since early relational patterns are central to that treatment approach. EMDR and trauma-focused practices should add a brief trauma history screen at intake, kept intentionally short, with the understanding that full trauma processing happens in session, not on a form.
Group therapy intake needs an added section on group readiness and prior group experience, plus explicit confidentiality expectations specific to a group setting rather than the individual-therapy language most base templates use.
The safest approach: keep your core five sections identical across every modality, then attach one modality-specific block of three to five extra questions. That keeps the form from becoming modality soup while still capturing what each clinical approach actually needs on day one.
How Often Should You Update Your Intake Form?
Treat your intake form as a living document, not a one-time build. Iterating based on what comes up in early sessions and trimming questions clients consistently skip keeps the form useful instead of bloated.
Set a recurring review, at minimum annually, to check three things: whether state licensure or reporting language has changed, whether your safety screening questions still reflect current best practice, and whether any fields have gone unused long enough to cut. A form that grows by one question every year and never sheds one becomes a client-abandonment problem within five years.
Trigger an off-schedule review any time you add a new service line, such as group therapy or a new specialty track, or any time a state where you practice updates its telehealth or minor-consent rules. Waiting for the annual review to catch a legal change is how practices end up out of compliance for months without realizing it.
The Template Trap Most Practices Fall Into
The conventional advice on intake forms treats them as a one-time build: download a template, fill in your logo, done. That’s backwards. The forms that actually work are edited quarterly based on what clinicians see going wrong in session one, not written once and forgotten.
The overrated piece of advice is comprehensiveness. Practices keep adding fields “just in case” until the form takes fifteen minutes and clients start leaving answers blank. A tighter form with sharp conditional logic beats a longer one every time, because the goal isn’t collecting more data, it’s collecting the right data before you need it.
What matters more than the questions themselves is the routing behind them. A safety-screen answer that sits unread in a chart until the session starts defeats the entire purpose of screening early. Prioritize the workflow that gets a flagged answer in front of a clinician within the hour, not just the wording of the question itself.
— serge
Automate Intake Delivery Without Losing the Clinical Detail
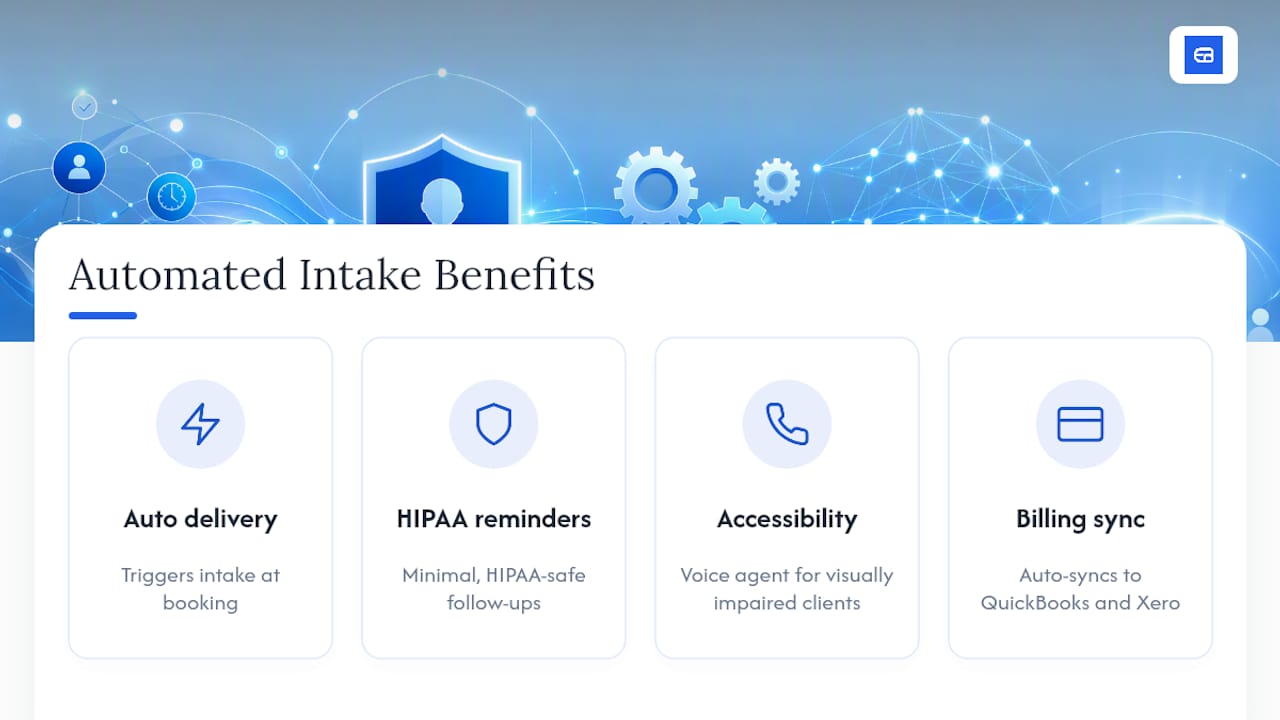
Building the perfect intake form solves half the problem. Getting it in front of the right client at the right time, with a reminder that doesn’t violate HIPAA and doesn’t fall on a receptionist’s to-do list, is the other half. Expressbook closes that gap by triggering your intake form automatically the moment a client books, then following up with minimal-content reminders that keep front-desk staff out of the loop entirely.
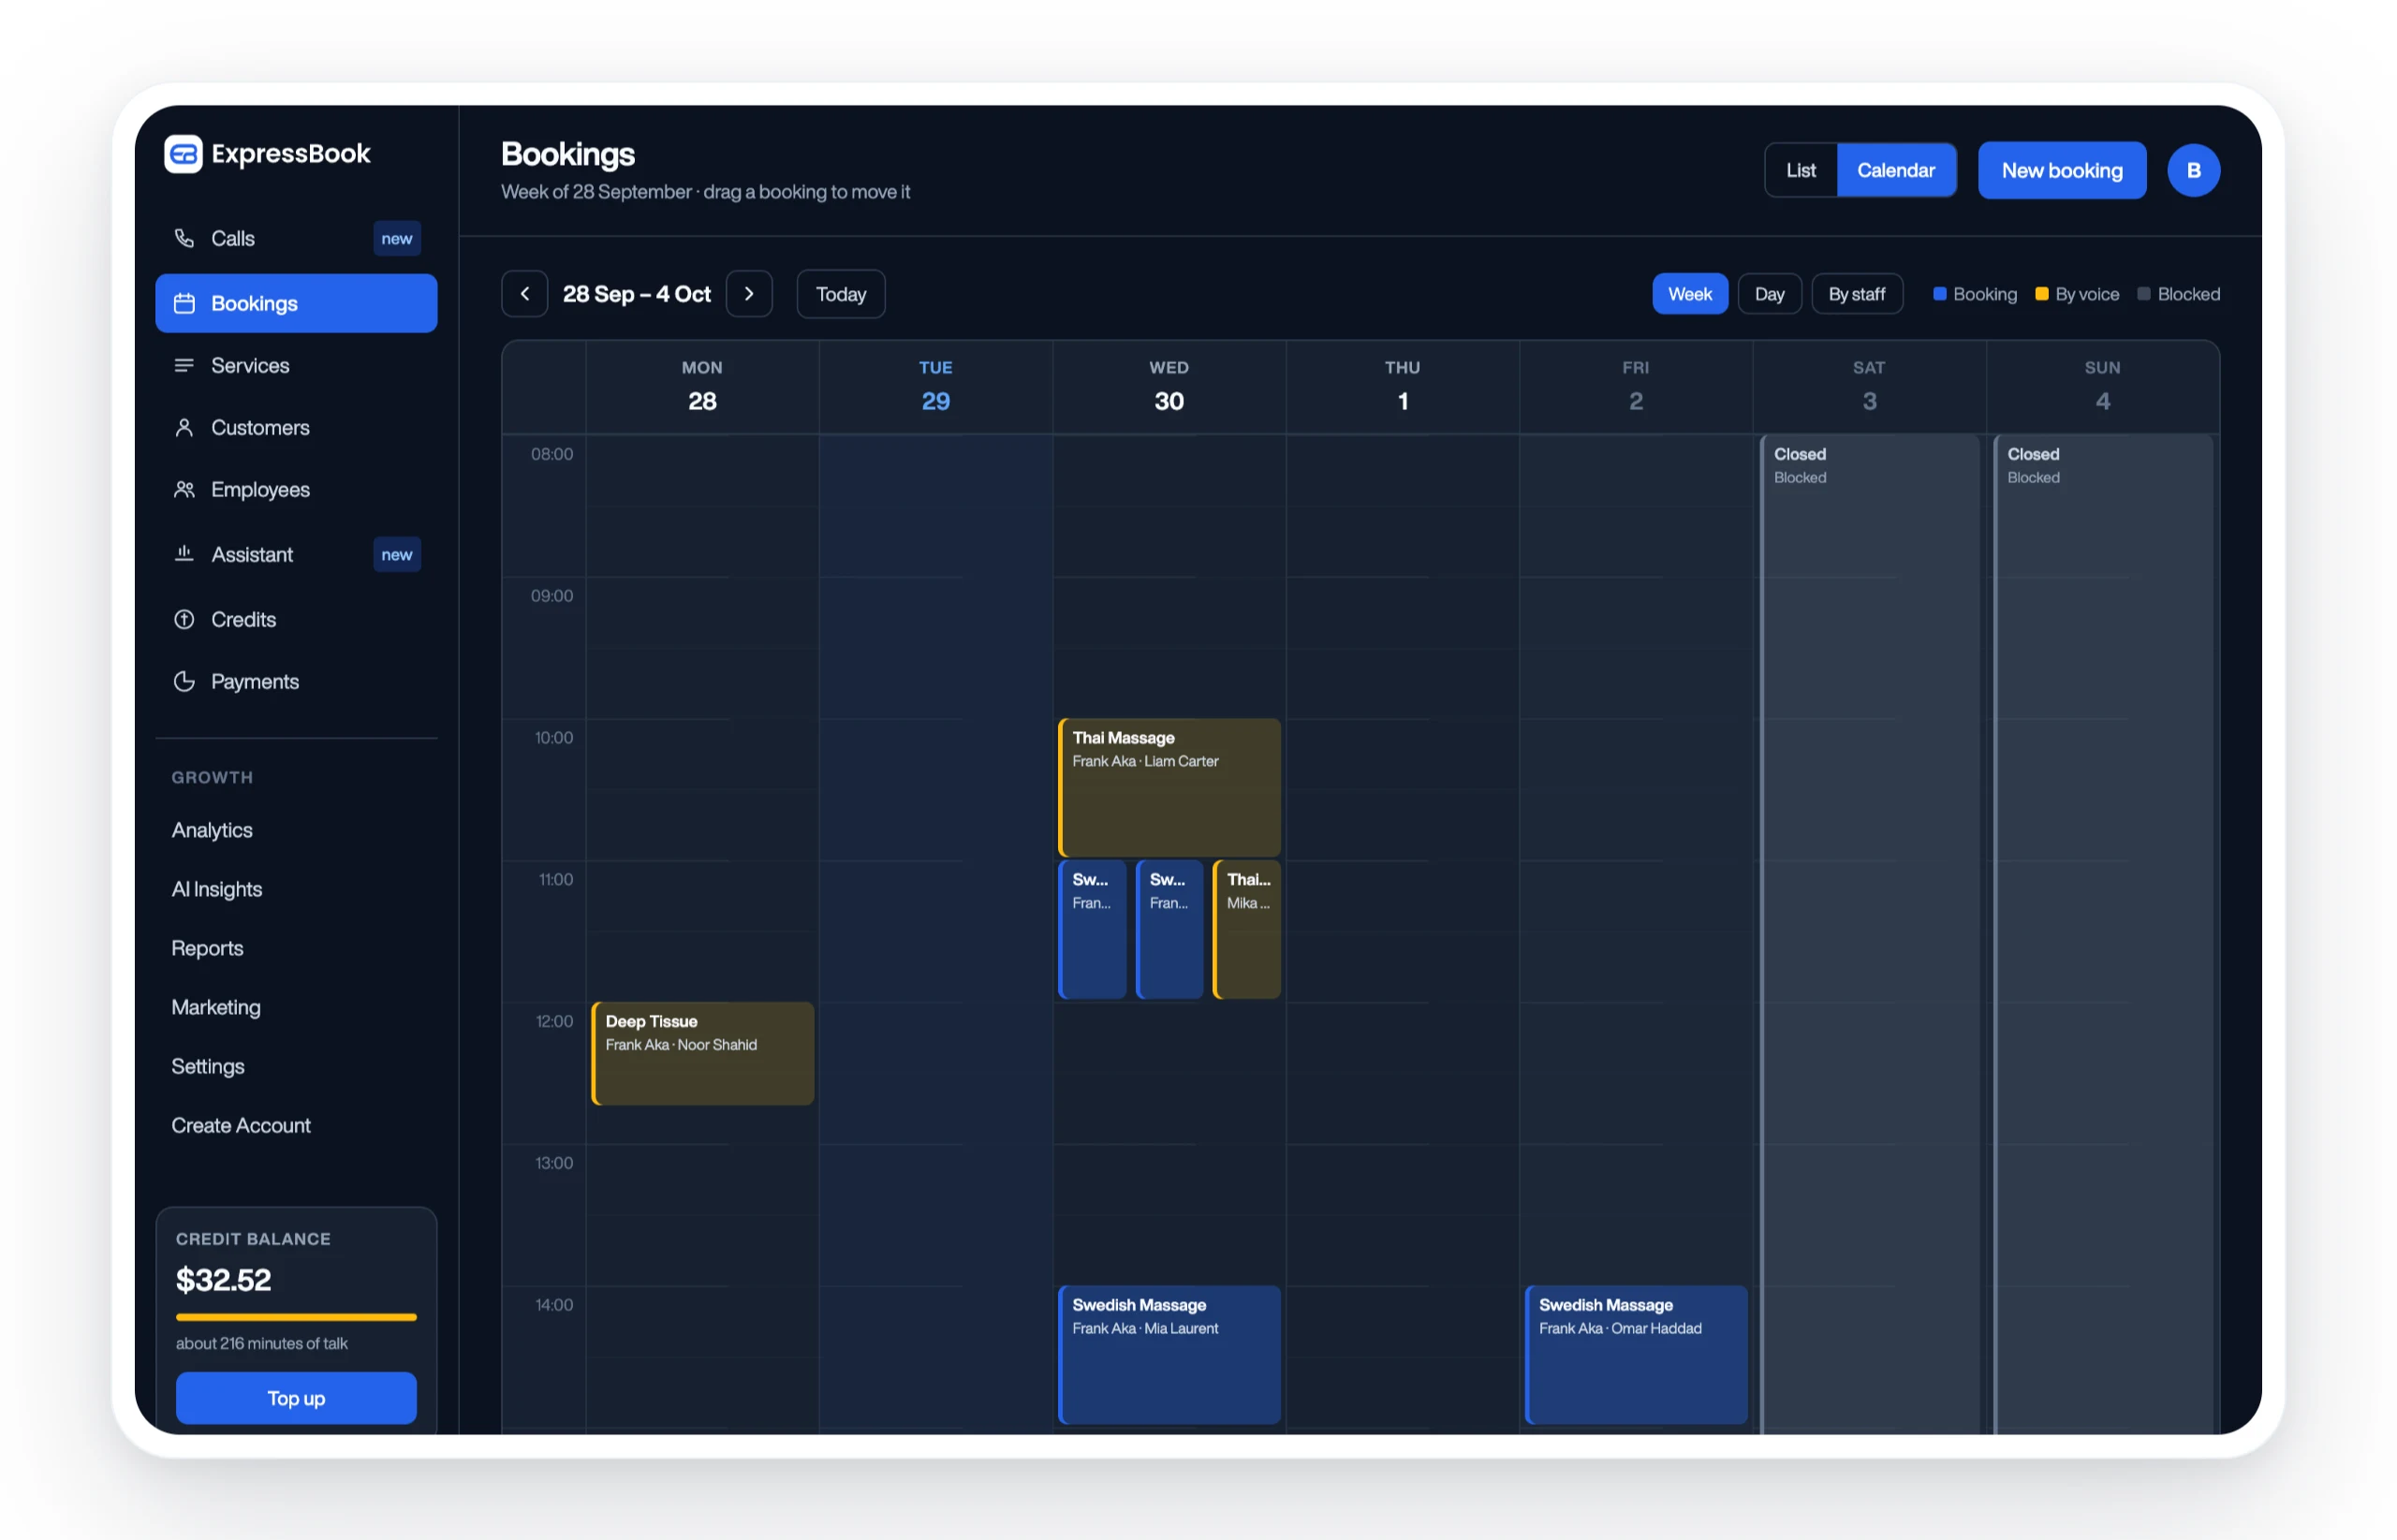
For a therapy or counseling practice, that means fewer no-shows from forgotten appointments and fewer clinicians walking into session one without having read the safety screen. Expressbook’s dedicated guide to HIPAA-aware appointment scheduling covers the compliance side directly, while the platform itself handles the operational side: a mobile app for both clients and admins, a voice agent that lets visually impaired clients book or ask questions without navigating a form alone, and automatic syncing of billing data into QuickBooks or Xero so nothing gets entered twice. Practices comparing online booking against manual scheduling consistently find the automated route cuts far more admin time than a paper-based intake ever could.
Expressbook has no subscription, so practices can test the workflow with a small credit top-up. Set up Expressbook and see how much front-desk time an automated intake and reminder system actually gives back.
This article is general information, not a substitute for advice from a qualified doctor. Consult a qualified healthcare professional about your own circumstances before acting on anything here.
Sources
- Is Text Messaging HIPAA Compliant? (HIPAA Journal)
- PMC article on digital health/tool adoption
- Therapy Intake Form Template Used by 5,000+ Therapists (Jane)